Laurie Kelley

Marvel-ous Hemophilia!

Doug and I treated ourselves to a night out— like teenagers! We saw the newest Spider-Man movie. As I child growing up with six brothers, comic books about superheroes in the 1960s were a mainstay; my mother even sewed Batman outfits for two of my brothers one Halloween. But we were Marvel fans all the way. And Spider-Man was the coolest. So armed with popcorn (my Kryptonite) and a diet Coke, we enjoyed this latest installment!

And with the greatest of timing, our archivist and famed researcher, Richard Atwood, sent us an essay about hemophilia and superheroes! Where and when does Marvel Comics mention hemophilia? Or DC Comics? Or any superhero comic or movie?

Mayfly

Mayfly is a nemesis of Wonder Woman [DC Comics]. Mayfly is a high-velocity hit woman who almost assassinates Diana, the name that Wonder Woman assumes. Mayfly suffers from a rare form of hemophilia. She is addicted to the drug Velocity-9. Wonder Woman captures the evil Mayfly. While imprisoned, Mayfly ends her own brief life. The type of hemophilia and its treatment are never revealed.

William Moulton Marston first introduced the super heroine character Wonder Woman in the 1941 DC Comics ALL-STAR COMICS #3. Mayfly, the fictional character with hemophilia, appears in the September 1993 (Vol. 2, #78) and the November 1993 (Vol. 2, #80) issues of DC Comics titled Wonder Woman.

Harmon Furmintz

Harmon Furmintz is only 15 when he graduates from Stanford University. Because of his biochemical genius, he is considered a prodigy – even superhuman. In 1940, Harmon becomes a candidate for a top-secret military project, but is rejected because he has a genetic deficiency: hemophilia. This rejection hurts his pride. The military project goes on to develop the super soldier named Captain America [Marvel Comics]. Harmon pursues genetic knowledge. In the 1950s, he works with Howard Stark in his biochemical division. Harmon, who is emotionally stunted, becomes the Chief Executive Officer of Genetech, at its superhuman genetic research complex in Sayville, Long Island. The company, under Harmon, develops the New Warriors, superhumans who are called “The Heroes for the 90s” with enhanced minds and bodies by biochemical, biomechanical, and biosurgical means. Furmintz continues to call himself a hemophiliac, and is afraid of being physically hurt.

The New Warriors was originally published by Marvel Comics in The New Warriors #1, #2, #3, #4 and in Thor #411, #412, then was compiled in a 1992 book by Marvel Comics titled The New Warriors: Beginnings.

Michael Morbius

Dr. Michael Morbius, winner of the Nobel Prize, is the foremost biochemist in Europe with his own laboratory. He is dying of a rare blood disease that dissolves blood cells. He conducts his research on a yacht in international waters to avoid regulators and to ensure security. His experiments with bat fluids prove to be ineffective. He combines the bat extract with electrical shock, which turns him into a living vampire who hungers for blood. Morbius now has hollow bones and underarm gliders, plus fangs, claws, and a pug nose. He leaves his girlfriend to visit the Cornell Medical Center in New York City. Morbius, who wants to quench his thirst for blood, fights with Spider-Man, a worthy adversary. The electrical shock treatment to create blood cells seems more like dated Frankenstein technology.

The Marvel antihero character Morbius has an interesting origin story that does not change much from its original 1963 telling in Marvel Comics (in Amazing Spider Man #101, #102; Marvel Two-in-One #15; Spider-Man Family #5) to its 2021 re-telling (in Morbius: Bond of Blood #1), that were compiled in the 2021 book titled Marvel-Verse: Morbius. The 2022 movie based on the comics is titled Morbius and stars Jared Leto as the title villain, plus has a supporting cast of millions of bats. The movie has updated DNA technology for genetic engineering, along with computer-generated special effects. The mixture of human DNA with vampire bat DNA into a serum, when injected into Morbius, gives him fangs and claws, plus echo location, and makes him hungry for blood. Morbius becomes a murderer in New York City. The book has a For Ages 10+ rating. The movie has a PG-13 rating.

[WARNING: Injecting vampire bat DNA is NOT a treatment for hemophilia!]

Oswald Angelone

Oswald Angelone is a pale, 20-year-old with hemophilia. His mother, who gave Oswald his name, is protective of her son. His father is Christopher Angelone, or Big Chris, the Sicilian-American mob family boss who runs his cocaine operations out of Miami. Oswald is called “Hemo.” He takes pills as treatment. There are questions regarding Oswald’s ability to eventually assume the role of Don. Big Chris sends his only son to the Central American country of Santa Morricone to assassinate El Presidente Leopoldo Luna, who supplies the cocaine. For protection, Barracuda accompanies Oswald. Barracuda decides to double-cross Big Chris for personal gain. After realizing that Big Chris does not value his son’s life, Oswald instead kills his father. But when Barracuda congratulates Oswald on becoming “Don Hemo” with a slap on the back, Oswald bleeds to death with blood gushing from his mouth.

The original Marvel comics were published as Punisher Presents: Barracuda Max #1, #2, #3, #4, #5, then compiled in the 2007 Marvel book titled The Punisher Presents Barracuda. The book has an Explicit Content warning for its language and sexual content.

Tom Morrell

Tom Morrell is a skinny, left-handed, high school senior. His single mother Brenda worries about him. Besides having hemophiliac, Tom suffers from over a dozen syndromes including diabetes, amyotrophy, and grand mal epileptic seizures. His daily routine of meds includes refrigerated shots and pills. Tom, who wears a special wrist alarm, is called “Gimp” at school. He awkwardly meets a new student named Angela Dirst, but he cannot express his feelings. When Tom is struck by a Mack truck, he first feels tired, then gains superpowers. So he claims, “I’m cured.” He wants to be a superhero, and even tries on a spandex suit. When Angela punches Tom in the nose for spying into her bedroom window, he bleeds. He falls, separates his shoulder, and fractures his collarbone. Brenda does some research to speculate that Tom’s body absorbs energy from crashes, then uses that energy to fight his diseases. She suggests that Tom allow a truck to run over his arms. With his arms in casts, Tom has lunch with Angela.

In this 2005 DC comics graphic novel titled Kinetic, the protagonist reads a copy of Kinetic, wishing for superpowers. He is an adolescent with hemophilia who is uncomfortable talking to young females. There is no mention of factor concentrate to treat his hemophilia, or Sharp’s containers for his used syringes. Dealing with high school has more than enough problems for any adolescent.

[WARNING: Being hit by a truck is NOT a treatment for hemophilia!]

PART 2 in two weeks!

References:

Jose Aguilar, Jovenes vampiros. El códice secreto. versos y trazos, 2007.

Anonymous, Stellar Guardians. Genentech, 2025.

Scott Beatty, Wonder Woman: The Ultimate Guide to the Amazon Princess. DC Comics, 2003.

Simon Boulerice et Eve Patenaude, Papier Bulle. Alice Jeunesse, 2023.

Kim Chilman-Blair and Shawn DeLoache, What’s Up with Louis? Medikidz Explain Haemophilia. Medikidz, 2011.

Garth Ennis, The Punisher Presents Barracuda. Marvel, 2007.

Jennifer Grunwald, Marvel-Verse: Morbius. Marvel, 2021.

Fabian Nicieza and Tom DeFalco, The New Warriors: Beginnings. Marvel, 1992.

Frederick Peeters and Pierre Oscar Levy, Sandcastle. SelfMadeHero, 2011.

Kelley Puckett and Warren Pleece, Kinetic. DC Comics, 2005.

TV Doctors and Hemophilia

When I was growing up, “Emergency” was one of my favorite TV shows. On July 9, one of the stars, Randolph Mantooth, passed away at age 80. He seemed beloved by all. I wondered if hemophilia was ever addressed in the show. This made me think of this excellent article, “Television Doctors Treating Hemophilia” by our archivist Richard Atwood of North Carolina in a 2020 issue of PEN. Enjoy!

Randolph Manooth

 In the 1960s, highly rated primetime medical dramas contributed to the rising popularity of network television viewing. Between 1950 and 1980, there were 55 drama primetime series involving physicians on the three major networks (ABC, CBS, NBC). Many of these series had medical advisors on the set; plus, they had endorsements from medical societies. Viewers had high expectations for the accurate depiction of any medical problems, all embedded within a compelling storyline.

         These television doctor half-hour or hour-long dramas eerily followed the same script-writing formula: the cast included an older physician and a younger physician, surrounded by an assortment of minor characters. Rather than foster a mentoring relationship, the older and younger doctors experienced dramatic conflict: for example, experienced versus neophyte, or humane versus scientific. The medical dramas also provided some mystery: Could the physicians correctly diagnose and successfully treat the difficult medical condition introduced each week?

         Fictional physicians, portrayed by famous actors, treated patients with hemophilia in a few of these evening broadcasts. A critical look back at some of these television doctor dramas offers another perspective on the history of bleeding disorders.

Dr. Kildare

Frederick Schiller Faust, writing as Max Brand, introduced the fictional Dr. James Kildare in a Cosmopolitan short story in 1936. Subsequent serialized short stories about Dr. Kildare appeared in pulp magazines. Paramount released a Dr. Kildare movie in 1937. Then Metro-Goldwyn-Mayer bought the rights to the popular Kildare character, and released nine Dr. Kildare movies and six Dr. Gillespie movies between 1938 and 1947. Lew Ayres starred in the Kildare role, with Lionel Barrymore as the older Dr. Gillespie. Ayres and Barrymore continued their roles in the The Story of Dr. Kildare radio broadcast on the MGM network for 80 episodes from 1949 to 1951.

         Radio was still a popular medium when the “Mysterious Hemophiliac Patient” episode was broadcast on May 18, 1951. At Blair Hospital, Dr. Kildare and Dr. Gillespie evaluate an anonymous patient who is found to have pyloric cancer, along with undisclosed hemophilia. The patient is an abdicated king from a small European country. Presurgical treatment includes ovarian extract capsules for two weeks, plus an intramuscular injection of 30 cc of fresh blood serum. During surgery, the patient receives direct blood transfusions. The hemophilia proves to be a greater problem than the cancer, but the patient successfully recovers from the surgery. This treatment for hemophilia was more appropriate during the 1930s, yet inappropriate in the 1950s when more effective blood products, such as fresh frozen plasma or Fraction I, were used.

         Richard Chamberlain as Jimmy Kildare, and Raymond Massey as Leonard Gillespie revived the Dr. Kildare series on television from 1961 to 1966. In 190 episodes during five seasons, NBC aired the award-winning MGM television Dr. Kildare series on Thursday nights. Apparently this popular Dr. Kildare never treated a patient with hemophilia.

Medic

NBC broadcast the award-winning television medical drama Medic for 59 episodes over two seasons, from 1954 to 1956. The 30-minute program was filmed in black and white. It was the first television medical drama to focus on medical procedures. Richard Boone starred as Dr. Konrad Styner. In “A Time to Be Alive,” the episode broadcast on January 31, 1955, 11-year-old Davey Stinson falls off his bike and bumps his knee. Due to his hemophilia, Davey spends two weeks in the hospital, where he receives four pints of blood and a leg brace. Recovering at home, Davey falls and cuts himself with broken glass. Back in the hospital, Davey receives two units of antihemophilic plasma and six units of fresh blood. His physicians worry that Davey might develop antibodies and “become refractory” (now called having inhibitors) to the fresh blood and plasma. Meantime, Davey’s untested sister worries that she might be a hemophilia carrier. Davey recovers and becomes an honor student. This hemophilia treatment was appropriate for 1954, though the amount of blood given is worrisome for circulatory overload.

Ben Casey

In direct competition with Dr. Kildare, ABC broadcast 153 episodes of the award-winning Ben Casey series on Wednesday evenings during five seasons, from 1961 to 1966. Vince Edwards played Dr. Ben Casey, while Sam Jaffe was the older Dr. David Zorba. Unfortunately, Dr. Casey never treated a patient with hemophilia. Yet National Hemophilia Foundation chose Vince Edwards—often mistaken by the public to be a real doctor—as their celebrity spokesperson.

Marcus Welby, M.D.

ABC aired the award-winning Marcus Welby, M.D. for 169 episodes on Tuesdays over seven seasons, from 1969 to 1976. The hour-long popular program, rated number 1 in its second season, was filmed in color. The American Academy of General Practice endorsed the series. Robert Young starred as Dr. Marcus Welby, while James Brolin played the younger Dr. Steve Kiley. In “The Daredevil Gesture” episode, broadcast March 17, 1970, 17-year-old Larry Bellows is a high school senior who doesn’t want his classmates to know that he has hemophilia. Larry is hospitalized about four times a year for his hemophilia, and treated with AHF (antihemophilic factor) injections. His mother, suffering from guilt, is overprotective. His sister, though never carrier tested, refuses to ever have any children. Larry defies his mother to attend a science club hike into the California canyons. He hemorrhages into his left knee while assisting a classmate with a broken ankle. Dr. Kiley rushes to the canyon with concentrate and plasma to treat Larry, who finally admits to his classmates that he has hemophilia. This episode focuses on the psychological dilemma of an adolescent with hemophilia who strives for normalcy by overcompensating with reckless behavior.

         All bleeding disorders are considered rare. The popular medical dramas broadcast on network television from 1950 to 1980 rarely used hemophilia as an interesting disease of the week. This is surprising, knowing how the misconception of bleeding to death due to hemophilia has so often been used as a plot enhancer by fiction writers. The fictional doctors on television acted more like role models, often in dramatic tension with other doctors, rather than as cooperative medical mentors to each other. Their sometimes inappropriate hemophilia treatments highlight the fact that the bleeding disorder community needed better treatment, namely through government-funded comprehensive care at hemophilia treatment centers staffed by a multidisciplinary team of medical specialists. Regrettably, televised medical dramas never showed the important advancement in hemophilia treatment that arrived in the 1970s.

©LA Kelley Communications, Inc. www.kelleycom.com Reprinted with permission.

Publication: PEN 2.20

Motorcycles and Hemophilia

Dwip, oost-surgery

I grew up in a motorcycle family. Each of my six brothers had one; my father always had one, since he was a young man, and my uncle has owned and operated Hogan’s Cycle Shop in Agawam, Massachusetts for over 71 years. Motorcycles were a way of life in my household, and I even rode them at one point.

But we always knew they could be dangerous. Two of my brothers were in serious accidents that left lingering injuries.

Imagine having to use a motorcycle when you have hemophilia in a developing country. It’s a common and cheaper way to get around, especially when there are massive traffic jams in megacities like Delhi and Karachi. Helmets often are not required, and traffic can be gnarly—and dangerous.

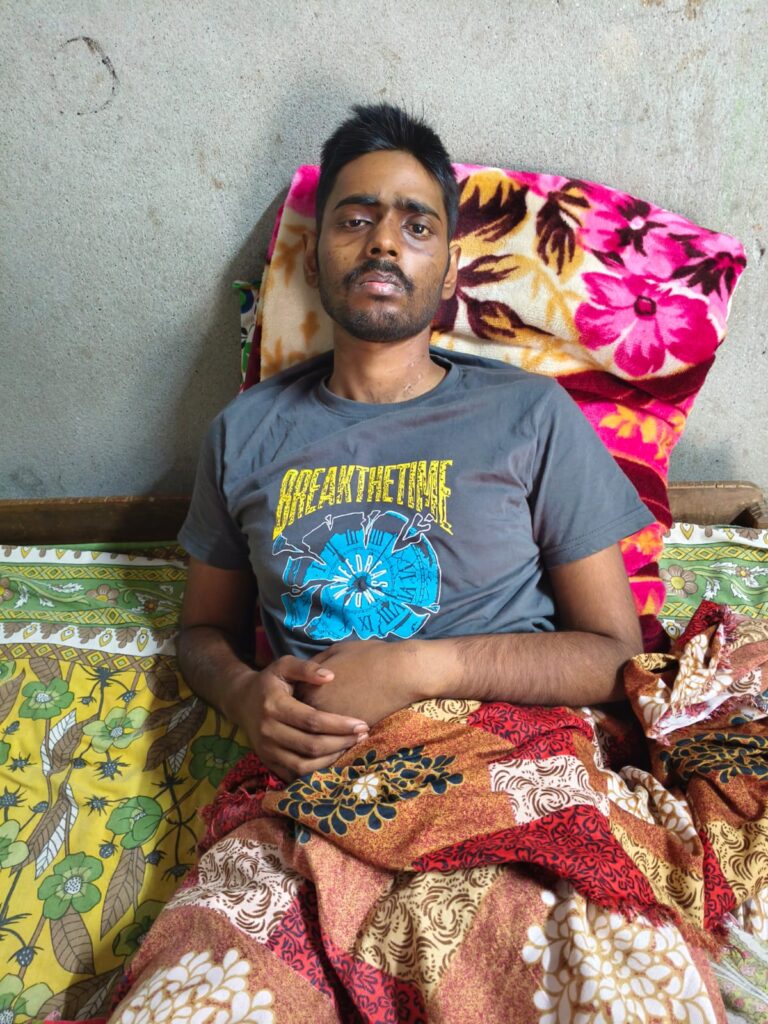
We recently funded surgery for a twenty-one-year old with hemophilia B from India. The Siliguri Hemophilia Society, a chapter in India, requested help for Dwip Biswas, from  Alipurdwar, West Bengal. On June 17 he suffered a road accident and sustained multiple traumatic injuries including a shattered femur bone, facial fractures, a nasal bone fracture and brain hemorrhage. He was admitted to Anandaloke Multispeciality Hospital, Siliguri, West Bengal. Dwip required multidisciplinary management involving orthopedics, neurosurgery, maxillofacial Surgery, and hematology, due to the complexity of injuries and the underlying bleeding disorder.

The treatment center estimated $5,500 for his surgery and further management. Dwip belongs to a very poor family. He’s in his second year of studies at school. His father is a vegetable farmer, his mother is a housewife and he has a married sister. It was impossible for his family to arrange such a huge amount. Sujata Minda, Secretary of the Siliguri Hemophilia Society, made a request to us, and we gladly helped. The Chennai Hemophilia Chapter helped arrange clotting factor.

Despite all his serious injuries, Dwip pulled through. Thanks to his medical team, and the Siliguri and Chennai chapters for their support. And thank to all of you, our readers. By checking our blog, and accepting our e-newsletter and ads, you indirectly support all our efforts to help those in need of surgery overseas.

It’s Summer Camp Season!

It’s summer camp season, especially for kids with a bleeding disorder! Attending summer camp is an excellent way for your child to engage in physical activities that appeal to him in a supervised setting designed for children with bleeding disorders.

At camp, your child will develop physical skill and build his self-esteem. Summer camp offers something that’s hard for parents to provide at home: a chance to fly away from under your protective wing. For no matter how you try to grant your child freedom, your shadow is everywhere in his young life, and your relationship with him is probably intense. Being on their own, without parents to please or look up to, is a step toward
maturity that most kids welcome.

It’s normal for parents to be nervous about sending their child away for a week. It may also be intimidating for your child at first. Feeling separation anxiety is normal for any child, especially if he has depended on you for infusions. If your child is socially immature or very dependent, camp can help
him mature.

How do you know if your child is ready for camp? Watch how he handles sleepovers. Is he homesick after only a few hours? Is he comfortable staying all night? Has he stayed with friends and neighbors as well as close relatives? If he handles sleepovers comfortably, he might be ready to try a bigger adventure.

Selecting a Camp
All hemophilia summer camps are not created equal. They have similarities and differences. Here’s how they are alike:

  • At a minimum, each camp is staffed with a nurse (usually an HTC nurse). Most have a social worker, physical therapist, and doctor on staff. Some have several nurses and doctors on staff with a fully outfitted medical clinic.
  • There are daily medical checks and infusions for injuries.
  • Most camps teach self-infusion—perhaps a good reason to send your child to camp.

Here’s how they differ:

  • Some camps are mixed, enrolling children with bleeding disorders and children with other blood disorders or disabilities.
  • Some are only for children with bleeding disorders.
  • Some are for both boys and girls.
  • Some allow families to stay, and some allow only siblings.
  • Most are for specific age groups.
  • Some provide extensive training for counselors, while others rely on untrained volunteers.
    Each camp has its own philosophy. They all offer different activities.

Consider the following list before deciding on a camp for your child. If one camp doesn’t meet your expectations, use these questions to find a camp that does:

  • How long does camp last?
  • Is camp only for children with bleeding disorders?
  • Are there any costs?
  • How is infusion taught?
  • Which age groups will attend?
  • Are families allowed to attend? Siblings?
  • What training do counselors receive? Do they have bleeding disorders?
  • Are there special events, like overnight camping, river rafting, or talent shows?
  • How is discipline handled? What rules are children expected to follow?
  • How is homesickness handled? Can my child call home, or is this discouraged?
  • What is the camp philosophy? Is there a religious, ethnic, or regional theme?
  • What is the ratio of counselor to campers? Suggested ratios are 1:6
    (one counselor to six campers) for ages 6 to 8; 1:8 for ages 9 to 14; 1:10
    for ages 15 to 17.
  • Who are the counselors? What is their training?
  • Who are the medical staff? Can I meet them personally?
  • What menu is offered? Can the camp accommodate special dietary needs?
  • Which activities are offered?
  • What are the protocols for medical emergencies?

Typical camp activities include archery, swimming, boating, canoeing, volleyball, board games, ping-pong, tennis, tower climbs, hikes, nature walks, woodworking, crafts, and scavenger hunts. Some camps o er rappelling, ropes courses, whitewater rafting, and horseback riding. If your child is interested in a particular activity, find out if the camp offers it. If possible, visit the camp to get a feel for where your child
will stay.

Camp is a big step: exciting, fun, and can make enormous positive changes in your child’s life!

Living with Hemophilia in the Philippines: Psychosocial Issues

Hemophilia is a bleeding disorder that many people in the Philippines still rarely hear about. When people think about hemophilia, they usually imagine bleeding, bruises, needles, and hospital visits. But honestly, the hardest part is not always physical pain. Sometimes it is the feeling of being misunderstood, left out, or treated differently your whole life.

For many boys growing up with hemophilia, there is always that question in their mind: “Why am I different?” While other kids freely run, climb, or play basketball outside, they are constantly reminded to be careful. Some grow up feeling limited before they even fully understand what is happening to them.

School can also become difficult emotionally. Instead of feeling accepted, some children with hemophilia experience teasing, bullying, or judgment from classmates. They get called “weak” because they cannot join rough games or sports. There are times when they simply sit and watch other children play while they stay on the side trying not to get hurt. That kind of feeling stays with a child.

Even teachers sometimes become too protective. Of course, they only want the child to stay safe, but constantly being excluded from activities can slowly affect confidence and self-esteem. Imagine growing up always hearing “you cannot do this” or “be careful” every single day. After a while, some children begin believing they are less capable than everyone else.

As they grow older, the emotional struggles become heavier. Some teenagers avoid making friends because they are tired of explaining their situation. Others become quiet and isolated because they feel nobody truly understands them. There are days when they act strong outside, but deep inside they are already emotionally exhausted.

Mental health is something rarely talked about in the hemophilia community. Many silently deal with anxiety, overthinking, fear, and sadness. Hospital visits become a normal part of life. So does the fear of sudden bleeding. Some patients even feel guilty, thinking they are becoming a burden to their family because treatment and care can be expensive.

And in the Philippines, that reality hits hard. Not every family lives near hospitals or treatment centers. Some travel for hours just to get medical care. Parents miss work, spend sleepless nights worrying, and carry stress that they rarely talk about. Mothers sometimes quietly blame themselves because hemophilia is inherited, while fathers pressure themselves to find ways to provide for treatment and daily needs.

Even siblings are affected too. Some learn to understand early why more attention is given to their brother with hemophilia. It changes the whole family dynamic in ways people outside the home rarely notice.

Then there is society itself. Many Filipinos still do not fully understand hemophilia. Some people think bruises are signs of abuse. Others immediately assume a person with hemophilia is weak or incapable. Those misunderstandings can be painful, especially for someone already struggling emotionally.

Finding work can also become stressful. Some adults with hemophilia hide their condition because they fear rejection or discrimination. Others constantly feel the need to prove themselves just to be treated equally.

But despite everything, people with hemophilia continue moving forward. They study, work, help their families, build friendships, and continue chasing dreams. Some may carry scars, pain, or trauma, but they also carry strength that many people never see.

This is why awareness matters. People with hemophilia do not only need medicine. They also need understanding, support, acceptance, and equal opportunities. Sometimes, a little compassion already makes a huge difference. Because the real battle of hemophilia is not only about stopping the bleeding. It is also about surviving the emotional, emotional, social, and psychological struggles that often stay invisible to everyone else.

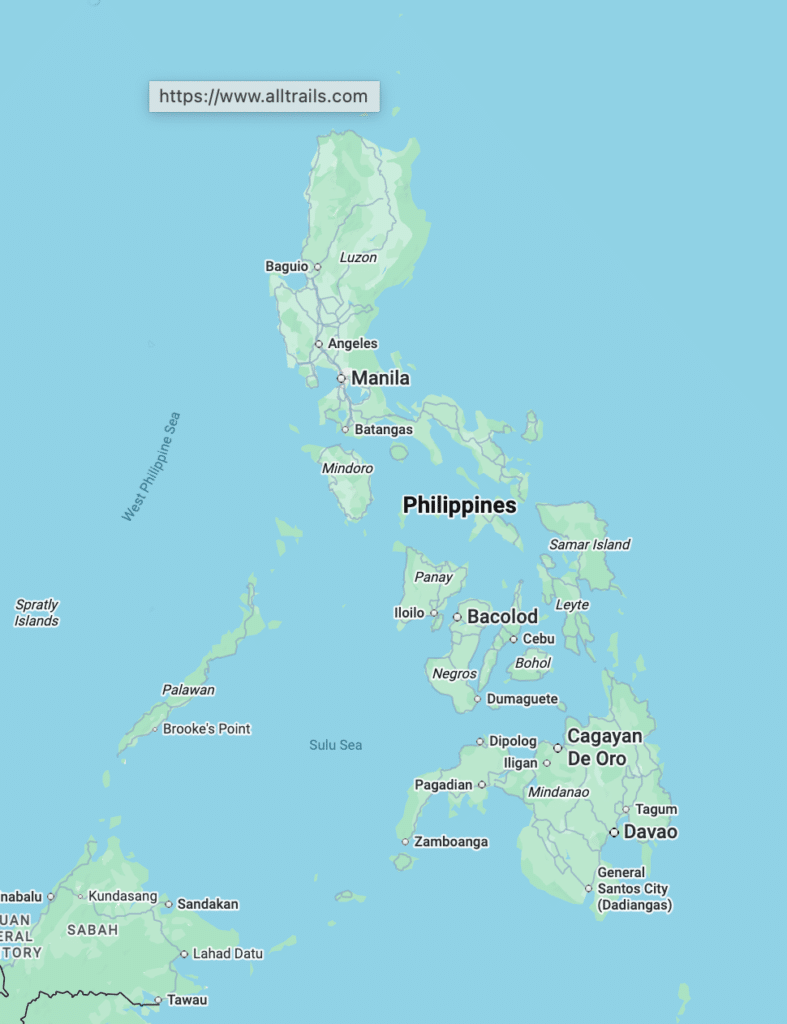
Jeffrey Castro Rodriguez is 44, has hemophilia A and lives in the Philippines. He graduated with a degree in psychology from Adamson University and worked as a call center agent after graduating in 2010. Growing up in a developing country where factor was never available, from a poor family with no stable source of income, his childhood was filled with hospital visits, financial struggles, and painful memories. He lost four brothers to severe bleeding during the 1990s. He himself is also a stroke survivor. Jeff now works from home as a Virtual Assistant while continuing his mission of serving the hemophilia community. He is vice-president of Blood Brothers Aid Inc., Dumaguete, where he actively educates and supports people with bleeding disorders.

HemaBlog Archives
Categories